Yuviwel and Navepegritide: What EMA’s Positive Opinion Means—and What It Does Not Prove
The European Medicines Agency’s medicines committee recommended Yuviwel (navepegritide) for children aged 2 years and older with genetically confirmed achondroplasia whose growth plates remain open. The positive opinion, adopted on October 15, 2026, is an important regulatory step—but it is not yet a European Commission marketing authorisation, a guarantee of national access, or proof that the medicine changes every important feature of achondroplasia.
The strongest short-term efficacy result comes from the 84-child APPROACH randomized trial. After 52 weeks, the adjusted difference in annualized growth velocity was 1.49 cm per year in favor of navepegritide (95% CI, 1.05–1.93). That supports a conclusion about linear growth over one year. It does not yet establish final adult height, broad disease modification, lasting mobility or quality-of-life gains, or complete long-term safety.
Searches for “navepegritide Yuviwel EMA approval” can blur several distinct decisions. The accurate sequence is: U.S. accelerated approval on February 27, 2026; a positive EU committee opinion on October 15, 2026; a European Commission decision still pending as of October 27, 2026; and, if authorisation follows, later national pricing and access decisions.
Quick answer: CHMP concluded that Yuviwel’s benefits support recommending EU marketing authorisation for a defined pediatric population. The opinion is not the final European Commission decision, and the pivotal endpoint was one-year growth velocity—not final adult height or comprehensive treatment of achondroplasia.
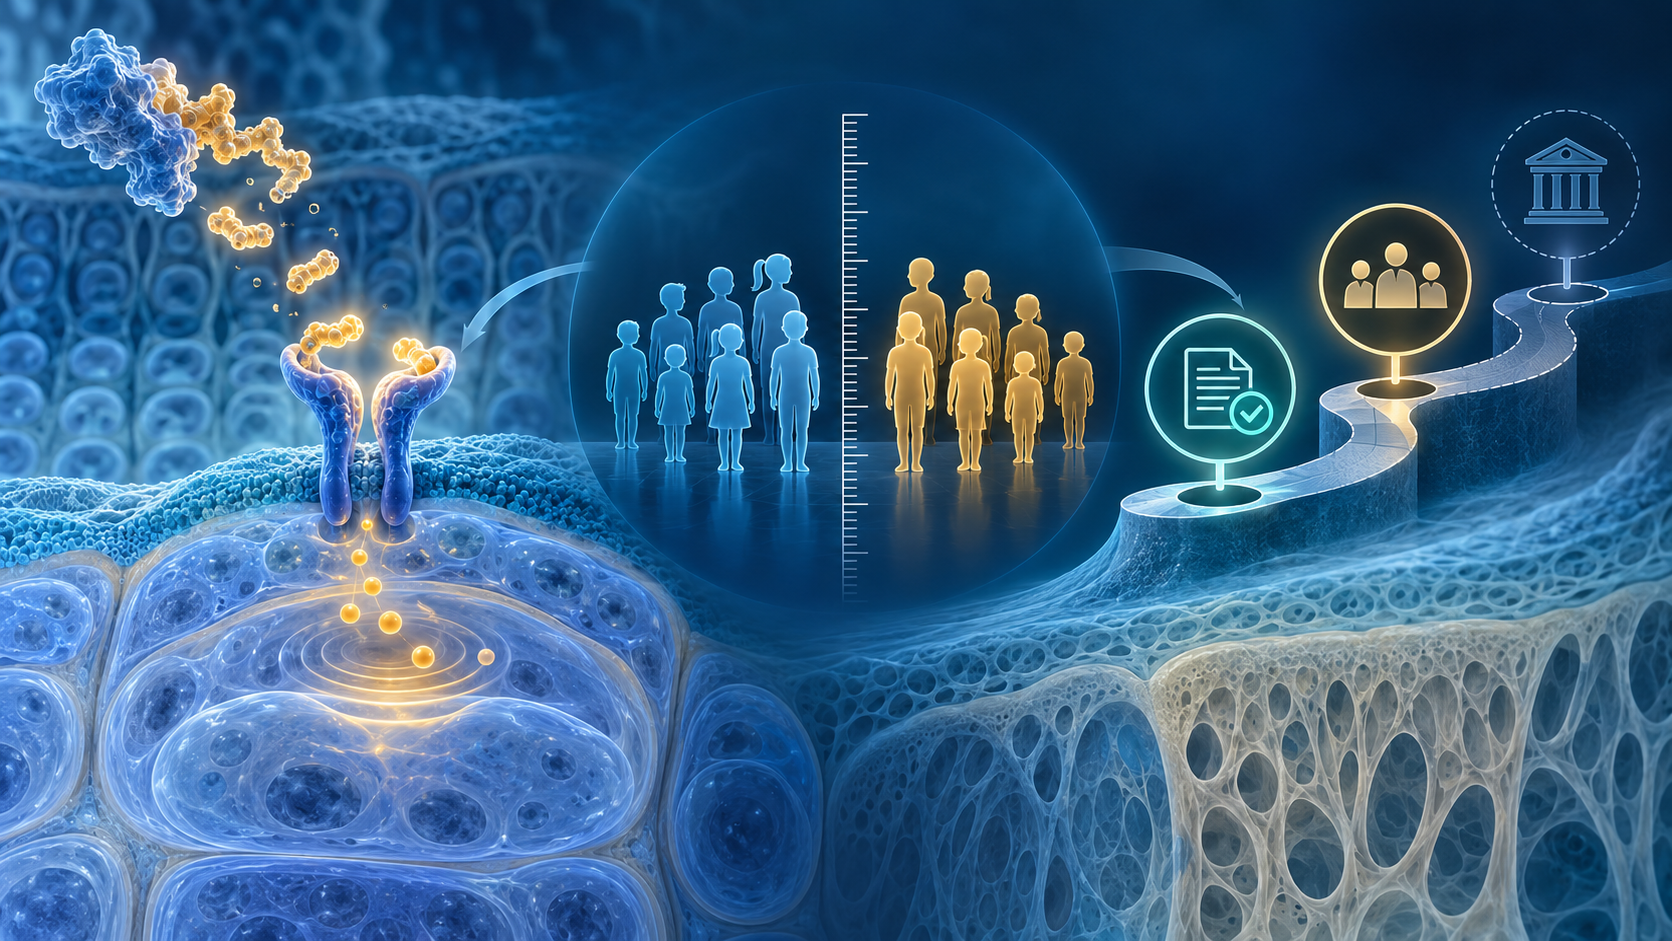
Navepegritide’s mechanism, the randomized growth result, and the regulatory pathway are related but separate. A plausible pathway is not clinical proof, and a committee recommendation is not the final EU authorisation.
What exactly did EMA’s committee recommend?
CHMP recommended granting a marketing authorisation for Yuviwel to treat achondroplasia in children aged 2 years and older whose epiphyses are not closed, with diagnosis confirmed by appropriate genetic testing.
The wording matters. A positive CHMP opinion is the scientific committee’s recommendation. The European Commission normally makes the legally binding decision for a centrally reviewed medicine afterward. EMA’s own opinion summary says the Commission decision normally follows within 67 days, but the opinion is published “without prejudice” to that decision.
Even a Commission authorisation would not mean immediate, uniform access across Europe. Price, reimbursement, health-technology assessment, rollout, and prescribing access can still differ by country. Regulatory authorisation answers whether the product may be marketed for an indication; national systems decide much of what practical access looks like.
| Stage | Status as of October 27, 2026 | What it establishes | What it does not establish | |---|---|---|---| | U.S. FDA review | Accelerated approval granted February 27, 2026 | Yuviwel may be marketed in the U.S. to increase linear growth in the labeled population | Verified benefit on final adult height or broad treatment of achondroplasia | | EU CHMP review | Positive opinion adopted October 15, 2026 | EMA’s scientific committee recommends EU authorisation | A final European Commission authorisation | | European Commission | Decision pending | If favorable, centralized EU marketing authorisation | Automatic reimbursement or immediate access in every country | | National access | Later country-level processes | Pricing, reimbursement, and practical availability | A new clinical efficacy finding |
This is why “EMA approval” is premature shorthand here. A clearer description is positive CHMP opinion pending the European Commission decision.
What is navepegritide, and how is it supposed to work?
Navepegritide is a once-weekly prodrug designed to release unmodified C-type natriuretic peptide, or CNP, over time. Released CNP binds natriuretic peptide receptor B (NPR-B), increasing signaling involved in growth-plate cartilage and endochondral bone growth.
Achondroplasia is usually caused by an activating FGFR3 variant. Excess FGFR3 signaling restrains growth-plate chondrocyte proliferation and differentiation. CNP–NPR-B signaling can counter part of that growth-suppressing pathway. EMA summarizes the intended result as promotion of chondrocyte differentiation and proliferation, thereby stimulating bone growth.
That mechanism is biologically coherent, but mechanism and clinical proof are not the same thing. NPR-B activation explains why increased linear growth is plausible. It does not, by itself, prove effects on neurological complications, sleep apnea, orthopedic surgery, mobility, pain, daily functioning, or every other manifestation of achondroplasia.
For the broader distinction between a peptide’s biological pathway and what human studies actually establish, see Peptide Research Status Explained and the Navepegritide database page.
Mechanism is not outcome: Releasing CNP and activating NPR-B supports a growth-plate hypothesis. Only clinical outcome data can show which benefits occur, how large they are, and how long they last.
What did the 52-week APPROACH trial show?
APPROACH was a phase 2b, multicenter, randomized, double-blind, placebo-controlled trial. It enrolled 84 children aged 2 to 11 years at 10 hospitals across seven countries. Fifty-seven were assigned to navepegritide and 27 to placebo.
The primary endpoint was annualized growth velocity at week 52. The least-squares mean estimates were 5.89 cm/year with navepegritide and 4.41 cm/year with placebo in the posted registry results. The adjusted between-group difference was 1.49 cm/year (95% CI, 1.05–1.93).
“Least-squares mean” means the result came from a prespecified statistical model that adjusted for treatment group, stratification factors, baseline age, and baseline achondroplasia-specific height z score. It is a group estimate, not a promise about an individual child.
The full analysis set included all randomized participants. Two children in the navepegritide arm discontinued treatment after parent or guardian withdrawal, one at week 26 and one at week 34. Their missing week-52 height measurements were handled with prespecified multiple imputation based on the placebo reference distribution. The registry therefore reports the model-based primary endpoint for all 57 and 27 randomized participants, while some figures based only on observed measurements have smaller denominators.
This reconciliation matters. “84 participants were analyzed” does not mean every participant supplied every week-52 measurement. The model preserved the randomized comparison while explicitly addressing missing data.
Why is growth velocity an intermediate endpoint?
Annualized growth velocity measures how quickly height changes over a defined period. It is clinically relevant, but it is not the same outcome as final adult height.
FDA treated improved growth velocity as an intermediate clinical endpoint reasonably likely to predict improved final adult height. That is why the U.S. decision used the accelerated-approval pathway rather than traditional approval based on verified final-height benefit.
FDA’s integrated review is unusually direct:
- one-year growth velocity supported a narrow indication to increase linear growth;
- the submitted evidence did not support a broad “treatment of achondroplasia” indication;
- improved final adult height must still be verified;
- other manifestations and complications were not shown to improve convincingly.
The required confirmatory study is intended to measure final adult height and includes disproportion, neurological complications, bone deformities, bone age, and sleep apnea among longer-term outcomes. FDA’s approval letter lists trial completion for September 2034 and final reporting for June 2035.
What is proven now: Navepegritide increased average annualized growth velocity over 52 weeks in the selected APPROACH population.
What remains unproven: That the observed one-year difference produces a meaningful improvement in final adult height or broad, durable improvement across achondroplasia-related health outcomes.
Did the trial prove benefits beyond growth?
No. The paper reported signals beyond growth, but the outcome hierarchy and FDA review call for restraint.
The prespecified multiplicity procedure included the primary endpoint plus five secondary endpoints. Achondroplasia-specific height z score improved after the primary growth endpoint succeeded. FDA concluded that the other prespecified secondary efficacy endpoints—including measures of physical function and quality of life—did not show statistically significant overall differences.
The paper also reported favorable estimates for tibial-femoral angle, mechanical axis deviation, fibula-to-tibia length ratio, and one physical-function measure in children younger than 5 years. Those skeletal alignment measures were exploratory, and the younger-child physical-function result was a subgroup finding. They can generate hypotheses and guide follow-up, but they should not be presented as confirmed broad clinical benefit.
The supplement makes the status of these analyses visible: lower-limb alignment and proportionality measures were listed as exploratory, observed denominators varied, and some health-related quality-of-life analyses involved subgroup-specific instruments. The trial also found no treatment effect on measured spinal curvature, and its authors acknowledged that it did not directly evaluate functional improvements, medical complications, or need for surgery.
This is a common evidence-literacy trap. A statistically interesting secondary or exploratory estimate can be real without carrying the same confirmatory weight as the prespecified primary endpoint. How to Evaluate Peptide Claims Online explains why the label “exploratory” is not a throwaway disclaimer.
What do the JAMA Pediatrics corrections change?
The corrected record should be used, but none of the three posted corrections changes the primary 1.49 cm/year result.
The article’s correction history says:
- January 5, 2026: open-access status was added.
- January 12, 2026: a rounding error in Figure 3 was corrected.
- March 2, 2026: the number of female participants in the text and Table 1 was corrected.
The corrected baseline counts are 26 female participants in the navepegritide group and 13 in the placebo group. The corrected PMC version links all three notices and includes the current article text and supplements.
Corrections do not automatically invalidate a paper. They do mean summaries should be checked against the corrected version rather than copied from an earlier release or sponsor announcement. Here, the corrections affect access, a rounded exploratory figure, and participant demographics—not the randomized primary growth estimate.
What safety findings deserve attention?
The 52-week trial did not reveal a large short-term safety imbalance, but the available dataset is too small and too short to settle uncommon or long-latency risks.
In APPROACH, no deaths occurred, no serious adverse event was considered treatment-related, and no protocol-defined symptomatic hypotension or fracture was observed. Injection-site reactions were tracked as adverse events of special interest. EMA identifies injection-site reactions and hypertrichosis as the most common side effects in its positive-opinion summary.
Several details complicate a simple “well tolerated” headline:
- Injection-site reactions: They occurred in both randomized groups and were generally mild in the trial, but local tolerability remains a product-specific adverse-effect category.
- Hypertrichosis: FDA’s broader safety review identified five reports among participants exposed to the therapeutic dose across blinded and open-label phases, with none at lower doses or in placebo. FDA judged the relationship probable, while noting variable timing and localized or generalized hair growth.
- Blood pressure: CNP has vasodilatory effects. APPROACH recorded no protocol-defined symptomatic hypotension, but surveillance timing did not always coincide with expected peak exposure. FDA found little evidence of clinically important resting hypotension, while retaining a warning because small samples and mechanistic/nonclinical data could not exclude risk.
- Immunogenicity: FDA reported treatment-emergent anti-navepegritide antibodies in 17% of participants exposed to the therapeutic dose for up to 3.25 years, and antibodies to the CNP component in 6%. The submitted neutralizing-antibody assay was not adequate to settle whether antibodies could neutralize navepegritide or native CNP. A separate postmarketing study with a validated assay is required.
The key point is not that these findings prove a major harm. It is that “no new safety signal in 84 children over one blinded year” is narrower than “long-term safety is established.” Our guide to Peptide Side Effects: Known, Unknown, and Overstated explains that distinction.
How selected was the trial population?
APPROACH studied a defined group rather than every child with achondroplasia.
Participants had genetically confirmed achondroplasia, open growth plates, no previous growth-promoting treatment, and a prior height measurement. Important exclusions included closed epiphyses, planned or recent growth-affecting surgery, severe untreated sleep apnea, conditions that could independently affect growth, significant cardiovascular findings, hemodynamic instability, chronic renal insufficiency, and other circumstances that could raise risk or confound interpretation.
Those criteria improve internal validity: they help the trial isolate a treatment effect. They also limit generalization. The randomized result most directly applies to children resembling those enrolled, under trial monitoring, during the one-year blinded period.
What evidence is still needed?
The evidence gap is not mysterious; regulators have named it.
The most important unanswered questions are:
- Does the growth-velocity difference persist through the remaining growth period?
- Does it translate into improved final adult height?
- Do body proportionality, mobility, daily functioning, or quality of life improve in a reproducible and clinically meaningful way?
- Does long-term treatment alter neurological, respiratory, orthopedic, or surgical outcomes?
- What uncommon or delayed adverse effects appear with larger and longer exposure?
- What is the true incidence and clinical relevance of neutralizing or cross-reactive antibodies when measured with a validated assay?
Open-label extensions can add useful durability and safety information, but they lose the protection of a concurrent blinded placebo comparison. The confirmatory final-height study and postmarketing immunogenicity work therefore matter more than another short-term mechanism argument.
The bottom line
EMA’s October 15, 2026 positive CHMP opinion means Yuviwel cleared an important scientific-review stage for a defined group of children with achondroplasia. It does not mean the European Commission has already granted marketing authorisation, and it does not settle later national pricing or access.
The pivotal evidence is credible and specific: in 84 randomized children, navepegritide improved annualized growth velocity by an adjusted 1.49 cm/year over placebo at 52 weeks. The result supports increased linear growth. It does not yet prove improved final adult height, comprehensive disease modification, durable mobility or quality-of-life benefit, or complete long-term safety.
The cleanest interpretation is also the least dramatic: navepegritide has a plausible CNP–NPR-B mechanism and a positive randomized result on a one-year intermediate growth endpoint. Regulators have moved forward while requiring the longer evidence needed to show what that difference ultimately means.
This article is educational only. It does not provide medical advice, treatment selection, dosing, injection instructions, sourcing, purchasing, or switching guidance.
Sources
- European Medicines Agency. Yuviwel EPAR page and CHMP summary of positive opinion. October 15, 2026.
- Savarirayan R, McDonnell C, Bacino CA, et al. Once-Weekly Navepegritide in Children With Achondroplasia: The APPROACH Randomized Clinical Trial. JAMA Pediatrics. 2026;180(1):18–25. doi:10.1001/jamapediatrics.2025.4771. Corrected January 5, January 12, and March 2, 2026. Supplements 1–3 reviewed with the corrected full text.
- ClinicalTrials.gov. NCT05598320: APPROACH trial record and posted results.
- U.S. Food and Drug Administration. NDA 219164 approval letter. February 27, 2026.
- U.S. Food and Drug Administration. NDA 219164 integrated review. February 2026.
- U.S. Food and Drug Administration. Yuviwel prescribing information. Revised February 2026.