How to Audit a Peptide Clinical Trial: Registry Records, Outcome Changes, and Missing Results
To read clinical trial results well, start with the trial registry—not the headline—and compare what was planned with what was eventually reported. A registry record can show when a study was registered, which outcomes were named, how many participants were expected, whether the study finished, and whether aggregate results were posted. It does not, by itself, prove that a peptide works, is safe, is approved, or was endorsed by a regulator.
This guide gives you a repeatable seven-step audit for peptide trials using ClinicalTrials.gov or another recognized public registry. It also shows how to compare the registry with a protocol, statistical analysis plan, journal paper, or company press release without treating every amendment as evidence of misconduct.
Quick answer: A credible audit follows the evidence trail in time: first registration → original outcomes → enrollment and status → record history → posted results → protocol or analysis plan → paper or press release. The important questions are what changed, when it changed, whether the change was disclosed, and whether the final claim matches the prespecified analysis.
Table of contents
- The seven-step trial audit
- Confirm trial identity and registration timing
- Save the first registration
- Compare primary and secondary outcomes
- Audit enrollment and completion status
- Read posted results
- Check the protocol and analysis plan
- Compare the paper or press release
- Worked example: NCT03548935
- Audit checklist
- Frequently asked questions
The seven-step trial audit
Use the same order every time:
- Confirm the trial identity and registration timing.
- Save the earliest available registry version.
- Record the original primary and secondary outcomes.
- Compare planned and actual enrollment, dates, and completion status.
- Inspect the full update history for outcome or design changes.
- Read posted aggregate results, participant flow, and adverse events.
- Compare the registry with protocols, statistical analysis plans, papers, and press releases.
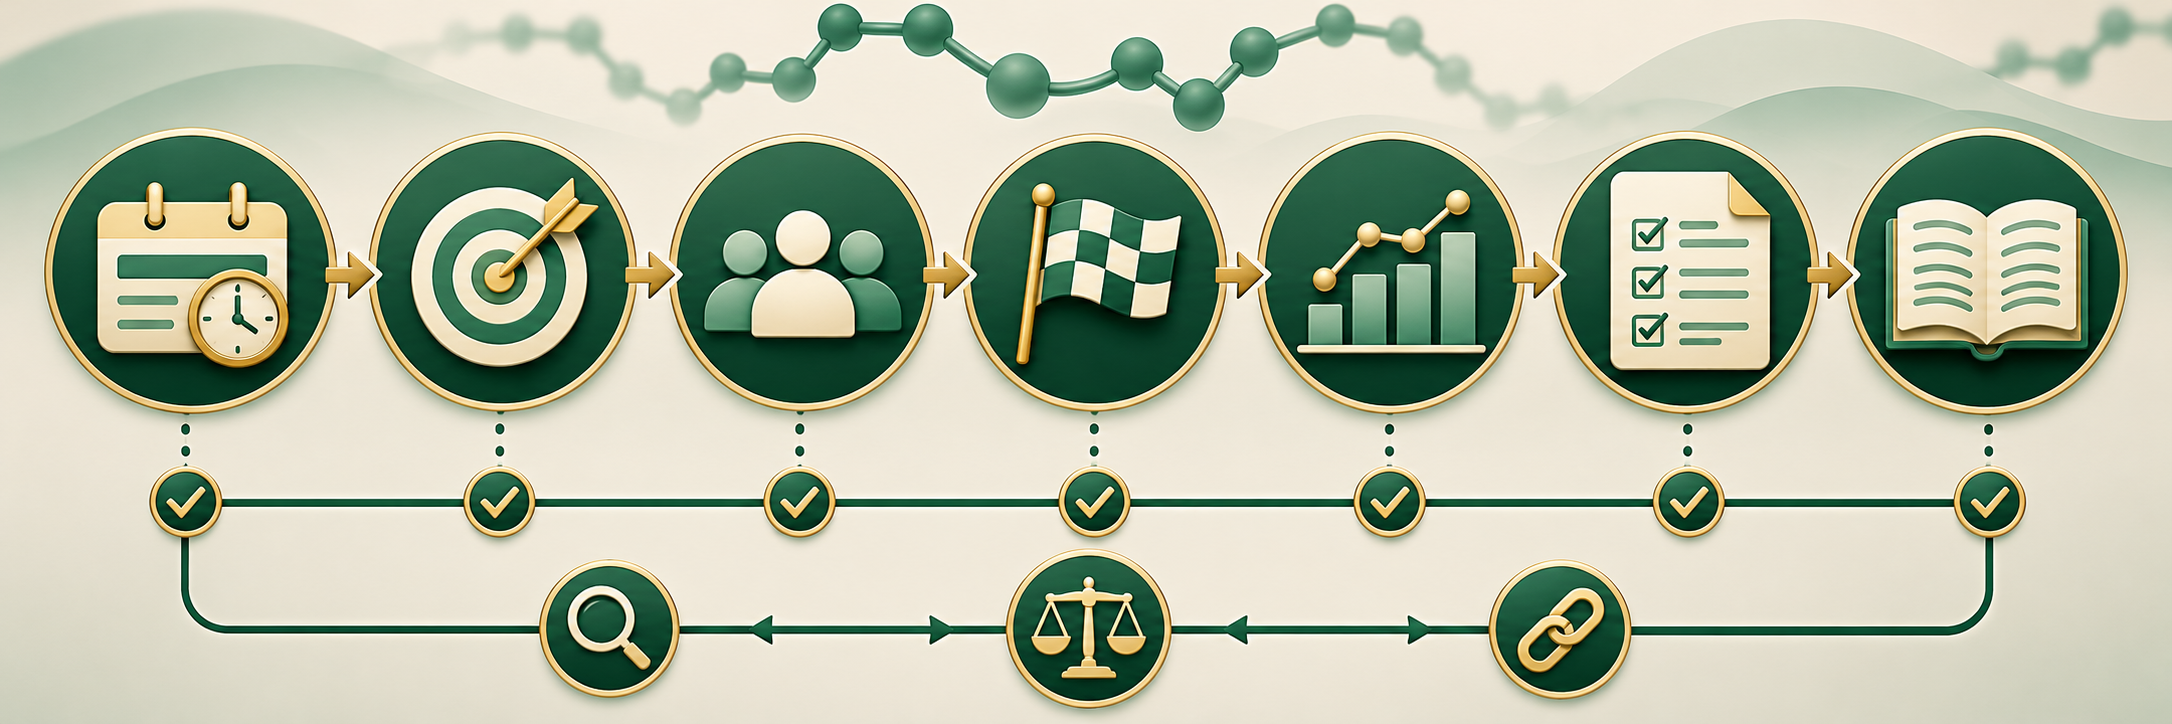
A defensible audit follows the record chronologically and compares each later claim with the study’s earlier plan.
This order matters. If you begin with a paper abstract or press release, you may unconsciously use the final story to reinterpret an earlier plan.
1. Confirm the trial identity and registration timing
The first check is whether you have the right trial and whether it was registered before enrollment began. Search by the registry identifier—such as an NCT number—not just the peptide name.
Record these fields:
- registry identifier and official title;
- sponsor and responsible party;
- intervention and comparator;
- study phase and design;
- study start date;
- first submitted and first posted dates;
- planned enrollment;
- primary completion and overall completion dates.
Prospective registration is important because it creates a public plan before results are known. The International Committee of Medical Journal Editors says trials should be registered in a public registry at or before the first participant gives consent for enrollment as a condition of journal consideration. Late registration does not automatically invalidate a study, but it weakens the registry’s value as a timestamped record of prespecification.
Audit question: Was the record publicly posted before the first participant enrolled? If not, label it retrospectively registered and look for a dated protocol or other contemporaneous plan.
2. Save the first registration, not just today’s record
The current registry page is a living document, so it may not show what readers would have seen when the study began. ClinicalTrials.gov preserves archival versions; use the record’s History view or archive to inspect them.
Save or note at least four versions when available:
- the first posted version;
- the version closest to first participant enrollment;
- the last version before primary outcome data collection ended;
- the version current when the main results were announced or published.
The National Library of Medicine explains that ClinicalTrials.gov records summarize study protocols, that some also contain results, and that the full history of changes remains available through the archive. That history is crucial because a current record can match the paper even if important changes occurred earlier.
A 2023 meta-research study of 1,746 registered randomized trials found that outcome changes were common in its sample and that some changes could only be detected by reviewing historical registry versions. The study does not show that every change was improper; it shows why looking only at the latest version can miss useful context.
3. Compare the original primary and secondary outcomes
Primary outcomes are the trial’s main prespecified tests; secondary outcomes answer additional questions and generally carry less evidentiary weight. Copy the full outcome definitions, not merely their labels.
For each outcome, capture:
- the exact measure;
- the metric or scale;
- the time point;
- the analysis population, if stated;
- whether it was primary, secondary, or exploratory;
- the date and version in which it first appeared.
“Change in symptoms” is not a complete outcome. A usable definition identifies which symptom scale, the comparison being made, and the measurement time. A paper can report a statistically significant result while answering a narrower or different question than the registered primary outcome.
What counts as an outcome change?
An outcome amendment is a question to investigate, not automatic proof of wrongdoing. Common changes include:
- adding or removing an outcome;
- promoting a secondary outcome to primary;
- demoting a primary outcome;
- changing the measurement tool or threshold;
- moving the assessment time point;
- changing the analysis population or estimand;
- replacing one outcome with a related surrogate.
The timing and explanation matter. A change made before enrollment, before unblinding, or because a measurement tool became invalid may be reasonable. A change made after outcome data were available, without a documented rationale, creates a more serious selective-reporting concern. The registry alone may not reveal why the change occurred, so check the protocol amendment, statistical analysis plan, paper, supplement, or author explanation.
Interpretation rule: Report the amendment neutrally first: what changed, when, and where it was disclosed. Judge its importance only after checking whether investigators could have known the result and whether the rationale was documented.
4. Audit enrollment, dates, and completion status
Enrollment and status fields tell you whether the analyzed study resembles the study that was planned. Compare planned enrollment with actual enrollment and identify which number is used in promotional claims.
Check:
- estimated versus actual enrollment;
- randomized, treated, analyzed, and completed participant counts;
- early termination, suspension, or withdrawal;
- reasons for stopping;
- primary completion versus overall completion;
- changes to eligibility criteria, arms, masking, or allocation.
The denominator is often where a claim changes character. “Eight of ten completers improved” is not the same as “eight of twenty randomized participants improved.” The registry’s Participant Flow section, when results are posted, helps reconstruct how many people entered each arm, received the intervention, completed follow-up, and were included in analyses.
A status of Completed means the study reached the registry’s completion definition. It does not mean the intervention succeeded. Terminated means the study stopped early after enrolling participants; the stated reason may involve recruitment, funding, safety, futility, strategy, or other factors. Unknown status can reflect an outdated record rather than a known scientific outcome.
5. Read posted results as structured evidence
Posted registry results are aggregate summaries, not a regulator’s endorsement or an independent peer review. On ClinicalTrials.gov, results may include participant flow, baseline characteristics, outcome measures, statistical analyses, and adverse events.
When learning how to read clinical trial results, work through these sections in order:
- Participant flow: Who entered, completed, and left each arm?
- Baseline characteristics: Were groups broadly comparable at the start?
- Outcome measures: Do results map to the registered outcomes and time points?
- Analysis details: Which participants were analyzed, and were estimates accompanied by confidence intervals?
- Adverse events: Are serious events and other events reported by arm, with denominators?
- Limitations or caveats: Were results submitted late, corrected, or accompanied by quality-control comments?
Do not reduce the audit to whether a p-value crosses 0.05. Look at the effect size, uncertainty interval, missing data, number of comparisons, and whether the analysis was prespecified. A small p-value does not repair a changed endpoint, a selective denominator, or a clinically trivial effect.
Quick answer: “No results posted” means the registry page does not contain structured aggregate results. It does not prove the study failed, was never published, or violated a reporting law. Some studies are not legally required to post results there, deadlines and extensions can apply, and records can be incomplete or outdated. Search publications and other registries, then describe exactly what is missing.
6. Look for the protocol and statistical analysis plan
The protocol explains the design; the statistical analysis plan explains how the data were intended to be analyzed. These documents can resolve ambiguities that a short registry field cannot.
Look in:
- the registry’s uploaded documents section;
- journal supplements;
- sponsor trial-transparency portals;
- regulatory review files;
- publication data-sharing statements;
- recognized repositories linked from the paper.
The strongest audit uses documents dated before unblinding or before the final analysis. Compare:
- analysis populations and handling of discontinuations;
- missing-data methods;
- covariate adjustments;
- multiplicity control and testing order;
- subgroup definitions;
- sensitivity analyses;
- planned safety analyses.
An analysis plan posted after results were known can still be informative, but it offers weaker evidence of prespecification. Record the document date rather than calling it “prespecified” by assumption.
7. Match the paper or press release back to the record
The final claim should be no broader than the population, comparator, endpoint, and follow-up that were actually studied. Build a simple side-by-side table.
| Audit field | Registry or protocol | Posted results | Paper or press release | |---|---|---|---| | Primary outcome | Exact definition and time point | Reported estimate and denominator | Headline conclusion and analysis | | Enrollment | Planned sample | Actual participant flow | Number described or analyzed | | Population | Eligibility criteria | Baseline characteristics | Population named in the claim | | Comparator | Placebo, active control, or none | Arm-level results | Comparator acknowledged or omitted | | Safety | Planned collection | Adverse-event tables | Safety language and follow-up | | Timing | Registration and amendments | Results posting date | Publication or announcement date |
Company releases and investor decks are useful as claims to verify, not as substitutes for the underlying record. Watch for relative effects without absolute numbers, responder percentages without denominators, emphasis on a favorable secondary outcome, subgroup findings presented as if they were primary, or “met its endpoint” language without the size and uncertainty of the effect.
Worked example: NCT03548935 (STEP 1)
The semaglutide STEP 1 record shows how the audit works without implying that one registry page settles every scientific question. Semaglutide is a peptide-based GLP-1 receptor agonist, and the identified record is ClinicalTrials.gov NCT03548935.
The current record reports:
- first submission on May 25, 2018;
- study start on June 4, 2018;
- first posting on June 7, 2018;
- Phase 3, randomized, parallel, masked design;
- actual enrollment of 1,961 participants;
- primary completion on March 30, 2020;
- results first posted on August 11, 2021;
- two primary outcomes related to percentage body-weight change and the proportion achieving at least 5% reduction at week 68.
The main paper, Once-Weekly Semaglutide in Adults with Overweight or Obesity, links to the same NCT number. That identifier is the bridge between sources.
An audit would now:
- open the earliest registry version and confirm which outcomes were present before or near enrollment;
- compare the original planned enrollment with the final 1,961;
- verify that the paper’s primary endpoints, week-68 timing, population, and comparator match the registry;
- inspect participant flow and adverse events rather than relying on the abstract;
- check the protocol and statistical analysis details for estimands, missing-data handling, and multiplicity;
- note that the first public posting occurred three days after the recorded study start, rather than describing the record as prospectively public without qualification.
This example is about method, not treatment advice. The registry and paper must be interpreted alongside regulatory documents and broader evidence when evaluating clinical use.
How to interpret preclinical, regulatory, and commercial evidence
Evidence types answer different questions and should not be blended into one confidence score.
- In vitro evidence can show binding, potency, or an effect in cells. It does not establish patient benefit.
- Animal evidence can support biological plausibility and justify human testing. It does not substitute for registered human outcomes.
- Human registry information shows that a study was planned or conducted and may show aggregate results. Registration alone does not establish efficacy or safety.
- Peer-reviewed publications add methods and expert review, but they still require comparison with the earlier plan.
- Regulatory records can show agency findings, approval status, or required labeling. Trial registration is not FDA approval.
- Commercial materials show how a sponsor presents the evidence. They are not independent adjudications.
For a broader evidence ladder, see Peptide Research Status Explained. If the study is an early human trial, When a Peptide Enters Phase 1: What It Means explains why human dosing is a milestone rather than proof of benefit. For claim-checking beyond trial registries, use How to Evaluate Peptide Claims Online.
A compact peptide-trial audit checklist
A good audit is reproducible: another reader should be able to follow your links and reach the same factual comparison.
- [ ] Correct registry identifier and intervention
- [ ] First posted date compared with first enrollment
- [ ] Earliest available primary and secondary outcomes saved
- [ ] Outcome definitions include metric and time point
- [ ] Planned enrollment compared with actual enrollment
- [ ] Randomized, treated, completed, and analyzed denominators separated
- [ ] Primary completion and overall completion distinguished
- [ ] Full record history checked for amendments
- [ ] Amendment timing and rationale documented without presuming intent
- [ ] Posted results checked for participant flow and adverse events
- [ ] Protocol and statistical analysis plan dates recorded
- [ ] Main paper matched by registry identifier
- [ ] Press-release claims compared with endpoints and denominators
- [ ] Missing results described precisely, without assuming why
- [ ] Registration not described as proof of efficacy, safety, approval, or endorsement
Frequently asked questions
Does a ClinicalTrials.gov entry prove a peptide works?
No. It proves that a record exists in the registry. Depending on the record, it may describe a planned, recruiting, completed, terminated, or results-posted study. Effectiveness requires interpreting the actual results, design, uncertainty, and broader evidence.
Is changing a primary outcome research misconduct?
Not automatically. Outcomes can change for legitimate reasons. The key questions are when the change occurred, whether investigators could have seen outcome data, whether the reason was documented, and whether the paper disclosed the change.
What is the difference between primary and secondary outcomes?
Primary outcomes are the main prespecified tests used to answer the trial’s central question. Secondary outcomes address additional questions. A favorable secondary result generally should not be presented as if it were a successful primary result.
Why can a completed trial have no posted results?
Completion status and results posting are separate fields. The record may be overdue, exempt from a particular legal requirement, subject to an allowed delay, published elsewhere, or simply not updated. Check the jurisdiction, dates, publications, and other registries before drawing conclusions.
Can I audit a trial using only the journal paper?
No. The paper is a final report, while the registry and dated protocol show earlier plans. Comparing them is what reveals whether endpoints, analyses, or denominators changed.
Bottom line
The safest way to read a peptide clinical trial is chronologically and comparatively. Start with the earliest registry version, track outcomes and enrollment through the record history, inspect posted aggregate results and adverse events, then compare the protocol, analysis plan, paper, and promotional claims.
A registry is transparency infrastructure. It helps you ask better questions; it does not answer every question or certify that an intervention works.
This article is for general education and evidence literacy. It is not medical advice and does not recommend any peptide, treatment, or protocol.
Sources
- ClinicalTrials.gov: NCT03548935
- ClinicalTrials.gov: How to Read Study Results
- National Library of Medicine: What information can I find on ClinicalTrials.gov?
- ICMJE Recommendations: Clinical Trial Registration
- Holst et al. (2023), PLOS Medicine: Frequency of multiple changes to prespecified primary outcomes
- Wilding et al. (2021), New England Journal of Medicine: Once-Weekly Semaglutide in Adults with Overweight or Obesity