Did GLP-1 Drugs Reduce Persistent Opioid Use After Surgery? What 279,250 Matched Pairs Actually Show
A nationwide matched study found fewer later opioid prescription records after surgery among adults with type 2 diabetes exposed to GLP-1 drugs, but its administrative proxy and observational design cannot prove reduced consumption, pain, or addiction.
Did GLP-1 Drugs Reduce Persistent Opioid Use After Surgery? What 279,250 Matched Pairs Actually Show
A nationwide U.S. database study found that an administrative proxy for persistent postoperative opioid use was recorded in 15.01% of people exposed to a GLP-1 receptor agonist before surgery and 17.44% of matched controls. That is a 2.43-percentage-point absolute difference and a 14% relative difference, but it does not prove that GLP-1 drugs reduced opioid consumption, pain, addiction, or surgery-related prescribing.
Wu and colleagues published the peer-reviewed Article in Press in Scientific Reports on September 13, 2026. The study included adults with type 2 diabetes who underwent eligible procedures in the TriNetX U.S. Collaborative Network from 2016 through June 2025. After extensive propensity-score matching, the analysis contained 279,250 pairs.
The primary outcome needs to stay attached to every interpretation: it was at least one documented opioid prescription on postoperative days 91 through 365. It was not verified medication use, continuous opioid use, opioid dependence, pain relief, or confirmation that the prescription was related to the index surgery.

The study linked preoperative medication records with later opioid prescription records. It did not randomly assign treatment or measure a direct analgesic effect.
Quick answer: what did the GLP-1 postoperative opioid use study find?
The pooled association was statistically precise but clinically more modest in absolute terms than the relative-risk headline may suggest.
- GLP-1RA group: 15.01% had at least one opioid prescription documented on days 91–365.
- Matched control group: 17.44% had the same administrative outcome.
- Absolute risk difference: 2.43 percentage points lower with GLP-1RA exposure (95% CI 2.24–2.62).
- Relative risk: 0.86 (95% CI 0.85–0.87), equivalent to a 14% lower relative rate.
- Plain-language scale: about 24 fewer people per 1,000 had a qualifying prescription record in the exposed group.
That last conversion describes the observed cohorts. It should not be turned into a treatment benefit or a number needed to treat, because the study was observational and residual confounding remains possible.
Absolute risk versus relative risk: why both numbers matter
Relative risk describes proportional separation; absolute risk describes the size of the observed difference in the studied population.
An RR of 0.86 sounds like a 14% reduction. The underlying rates show what that means here: 17.44% minus 15.01% equals 2.43 percentage points. Both are mathematically valid descriptions of the same pooled result.
Neither number answers the causal question by itself. A narrow confidence interval means the estimate is statistically precise under the model. It does not guarantee that the estimate is free from confounding, exposure error, outcome misclassification, or systematic differences between institutions.
Evidence-literacy answer: Large databases can estimate an association very precisely. Precision is not the same thing as proof that the exposure caused the difference.
What exactly did the researchers measure?
The researchers measured coded healthcare events, not opioid-taking behavior. Preoperative exposure meant a documented GLP-1 receptor agonist record within the 90 days before surgery. The primary outcome meant one or more documented opioid prescriptions between postoperative day 91 and day 365.
Measured in the database
- adult status and a type 2 diabetes record;
- an eligible surgical procedure during the study period;
- documented GLP-1RA exposure within 90 days before surgery;
- recorded baseline characteristics used for matching;
- at least one qualifying opioid prescription record on days 91–365;
- coded secondary outcomes during that interval.
Not proven by the database
- that the prescription was filled or the opioid was consumed;
- that opioid use was continuous, frequent, or clinically problematic;
- that the prescription was for pain caused by the index surgery;
- how severe the person’s pain was or whether pain improved;
- that GLP-1RA exposure continued, at what dose, or with what adherence;
- that the observed association was caused by the drug;
- that the pooled result applies equally to every operation or anaesthetic technique.
Calling this outcome “persistent postoperative opioid use” is convenient shorthand, but the operational definition was much narrower: a later prescription record. That distinction is not pedantry. It changes what the study can honestly support.
How did propensity-score matching help?
Propensity-score matching improved comparability on recorded baseline characteristics, but it did not recreate random assignment. The researchers estimated each patient’s likelihood of preoperative GLP-1RA exposure from measured variables, then matched exposed and unexposed patients with similar scores.
This approach can reduce imbalance in measured factors such as demographics, diagnoses, comorbidities, medication history, and procedure-related characteristics. With 279,250 matched pairs, it also supports precise estimates.
It cannot balance information that was absent, incomplete, miscoded, or poorly measured. Important remaining possibilities include:
- unmeasured confounding: factors influencing both prescribing and postoperative opioid records;
- secular change: GLP-1RA uptake and opioid-prescribing practices changed across 2016–2025;
- healthcare engagement: people receiving newer metabolic drugs may interact with healthcare systems differently;
- adherence uncertainty: a medication record does not prove sustained GLP-1 exposure;
- outcome misclassification: one prescription is an imperfect proxy for persistent use;
- institution effects: hospitals differ in case mix, coding, follow-up, formularies, and opioid stewardship.
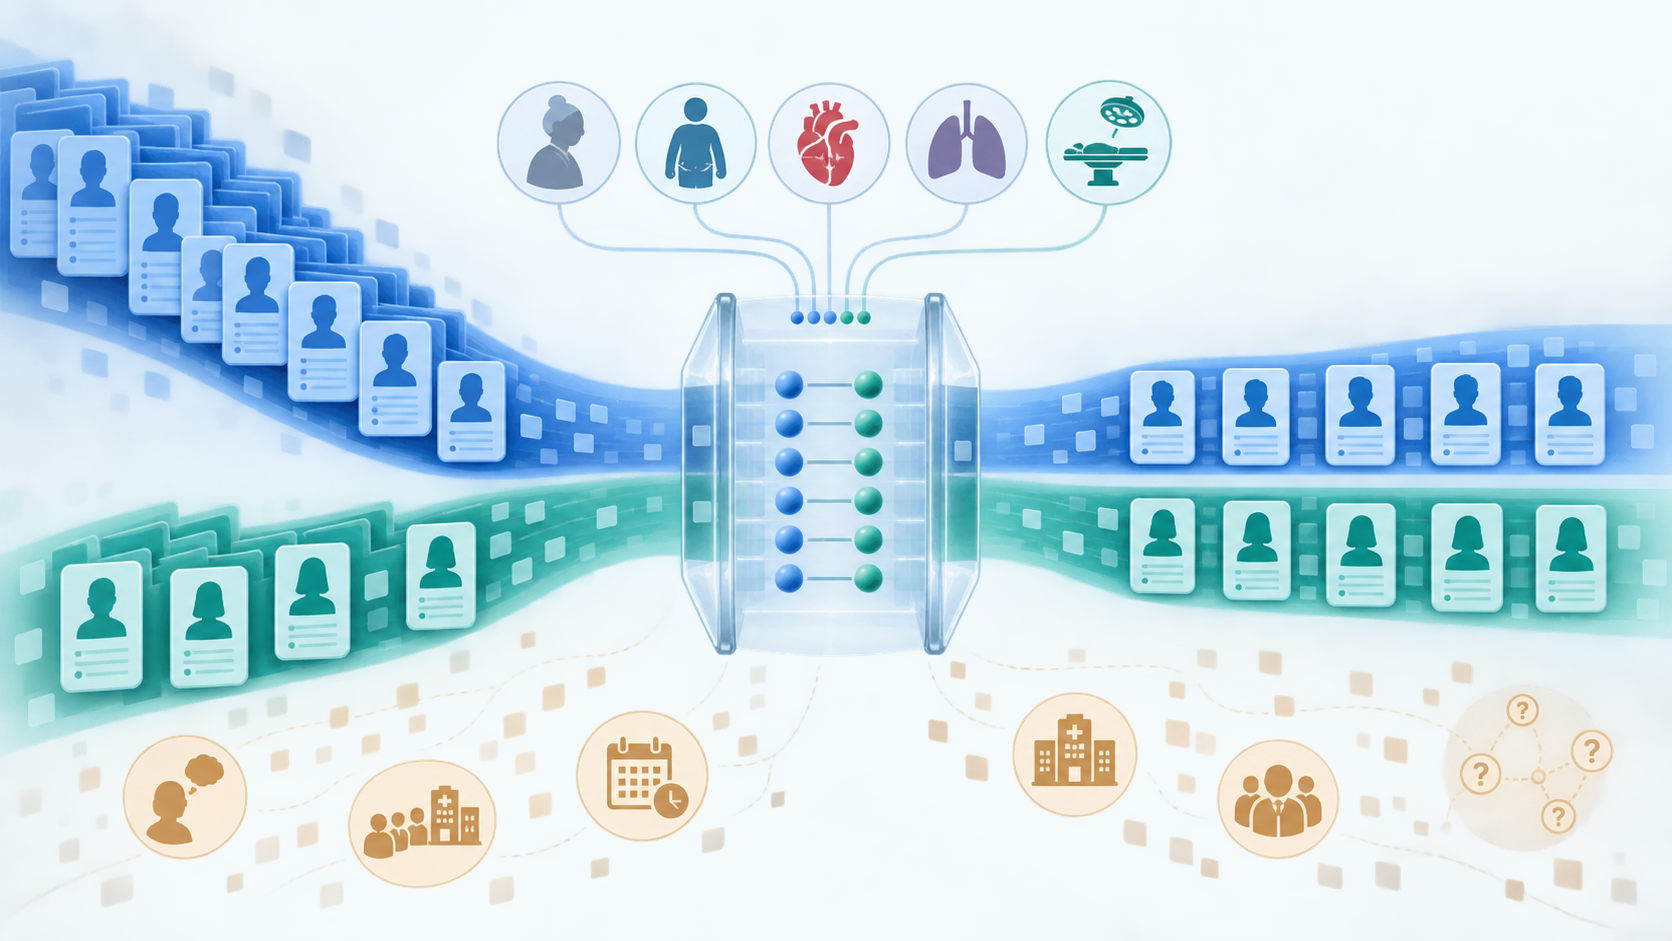
Matching can balance recorded variables. It cannot automatically correct for adherence, healthcare engagement, prescribing-era changes, institution-level practice, or other unmeasured factors.
Why does subgroup heterogeneity change the interpretation?
The association was not uniform, which argues against treating the pooled RR of 0.86 as a universal surgical effect.
The reported subgroup estimates included:
- Documented general anaesthesia: RR 0.99, with an FDR-corrected p value of 0.1128—near null and not statistically significant after correction.
- Regional anaesthesia: RR 0.94, a more modest association than the pooled estimate.
- Cardiovascular procedures: RR 0.85.
- Non-cardiovascular procedures: RR 0.95.
- Type 2 diabetes documented for at least five years: RR 1.00, indicating no association in that subgroup.
Composition matters. Cardiovascular procedures accounted for about 70% of the cohort, so they carried substantial weight in the pooled result. More than half of patients were classified under other or unknown anaesthetic technique, limiting any clean claim about general versus regional anaesthesia.
Subgroup analyses can be noisy, affected by coding, and vulnerable to multiple comparisons. They should not be mined for a winning explanation. Here, their main value is caution: the pooled association should not be generalized to all surgery, all anaesthetic approaches, or all people with type 2 diabetes.
Heterogeneity answer: A pooled average can be real as a summary and still be a poor description of several major subgroups.
What did the secondary outcomes show?
Chronic postsurgical pain, naloxone initiation, and opioid use disorder were also recorded less often in the GLP-1RA group, but these remain secondary observational associations.
The reported relative risks were:
- chronic postsurgical pain: RR 0.78 (95% CI 0.73–0.84);
- naloxone initiation: RR 0.84 (95% CI 0.81–0.86);
- opioid use disorder: RR 0.54 (95% CI 0.37–0.78).
Smaller relative risks do not automatically mean larger or more certain causal effects. These outcomes depend on diagnosis, prescribing, coding, healthcare contact, and clinical recognition. Naloxone initiation is not the same as overdose. An opioid use disorder code is not the same as systematic diagnostic assessment. Chronic postsurgical pain codes do not capture every person’s pain experience.
Secondary findings can generate hypotheses and show whether signals point in a similar direction. They do not repair the nonrandomized design or establish a treatment effect.
Did the study test why GLP-1 drugs might matter?
No. The authors explicitly stated that the study was not designed to test a direct analgesic mechanism.
Several biological ideas could motivate future research:
- altered inflammatory signaling;
- improved metabolic health or glycaemic control;
- changes in pain-processing pathways;
- effects on reward or opioid-reinforcement pathways.
Those are hypotheses, not measurements from this analysis. TriNetX records did not show that inflammation fell, pain signaling changed, reward circuitry was altered, or opioid reinforcement weakened. A plausible mechanism can make an association worth studying, but it cannot establish why the association appeared.
For context on why peptide medicines should be evaluated by product, mechanism, and evidence rather than category alone, see GLP-1 Peptides vs Research Peptides. Our guides to evaluating peptide claims online and understanding peptide research status provide broader evidence-literacy tools.
A practical appraisal checklist for observational perioperative studies
The fastest way to appraise a perioperative database study is to separate its target question from what its records can actually observe.
- Define the exposure. Was it a prescription, dispensing record, administration, active medication list, or confirmed adherence?
- Define the outcome literally. Is “use” based on a prescription, a refill pattern, patient report, toxicology, or consumption data?
- Check the clock. When did exposure, surgery, and outcome measurement begin and end?
- Inspect the comparator. Why might exposed and unexposed patients differ before matching?
- Audit matching. Which variables were balanced, and which clinically important factors were unavailable?
- Look for secular trends. Did treatment adoption, coding, or opioid-prescribing policy change during the study years?
- Check institution effects. Could hospitals or health systems differ in follow-up and prescribing culture?
- Read absolute and relative results together. A dramatic relative number can represent a smaller absolute difference.
- Inspect heterogeneity. Does the pooled estimate describe the largest procedure and anaesthesia groups?
- Keep mechanisms separate. Did the study measure the proposed pathway, or merely discuss it?
- Treat secondary outcomes as secondary. More endpoints create more opportunities for chance, coding artifacts, and selective emphasis.
- Ask what would change confidence. Replication, better exposure measurement, institution-adjusted analyses, negative controls, prospective designs, and randomized evidence answer different weaknesses.
What is the most defensible conclusion?
Preoperative GLP-1RA exposure was associated with fewer later opioid prescription records in a very large matched cohort, but the study did not show that GLP-1 drugs prevent persistent opioid consumption or directly relieve postoperative pain.
The headline result is numerically clear: 15.01% versus 17.44%, an absolute difference of 2.43 percentage points and RR 0.86. The evidence boundary is equally clear: retrospective EHR data, a prescription-based proxy, uncertain adherence, residual confounding, institution-level variation, and important subgroup heterogeneity.
This is a useful signal for research. It is not a medication-management conclusion.
Frequently asked questions
Did GLP-1 drugs reduce opioid use after surgery?
The study found fewer patients with at least one documented opioid prescription on days 91–365 after surgery. It did not confirm consumption or prove that GLP-1RA exposure caused the difference.
What does persistent postoperative opioid use mean in this study?
It meant at least one documented opioid prescription during postoperative days 91–365. It did not require continuous use, repeated fills, confirmed consumption, addiction, or proof that the prescription related to the surgery.
Was this a randomized clinical trial?
No. It was a retrospective propensity-score-matched cohort study using the TriNetX U.S. Collaborative Network.
Why isn’t matching enough to prove cause and effect?
Matching balances recorded characteristics included in the model. It cannot balance unknown or unrecorded differences, correct every coding error, or guarantee equivalent healthcare engagement, adherence, prescribing context, and institution-level practice.
Did the result apply across all surgery types?
No. The association was stronger in cardiovascular procedures than non-cardiovascular procedures, near null with documented general anaesthesia, and null among people with type 2 diabetes documented for at least five years.
Did the study show that GLP-1 drugs are analgesics?
No. The authors said the study was not designed to test a direct analgesic mechanism.
Source
Wu HL, Chen JT, Cata JP, Cherng YG, Tai YH, et al. “Perioperative glucagon-like peptide-1 receptor agonist exposure and persistent postoperative opioid use among adults with type 2 diabetes mellitus: a propensity score-matched cohort study.” Scientific Reports. Article in Press, published September 13, 2026. doi:10.1038/s41598-026-71924-1.
This article is for general education only. It does not provide advice about GLP-1 medication use around surgery, opioid management, pain treatment, or any decision to start, stop, continue, or hold a medicine.