Do GLP-1 Drugs Cause Nail Detachment? Why the Fourfold Headline Is Not a Causal Verdict
A 2026 EADV survey found much more onycholysis among GLP-1 users, but the new-onset analysis was null. Here is why the fourfold headline does not establish causation.
Do GLP-1 Drugs Cause Nail Detachment? Why the Fourfold Headline Is Not a Causal Verdict
No study has established that GLP-1 drugs cause nail detachment. A multinational survey presented at the European Academy of Dermatology and Venereology (EADV) Congress 2026 found onycholysis in 39.3% of GLP-1 receptor-agonist users and 8.7% of non-users with obesity and/or type 2 diabetes. That crude prevalence gap is striking. It is not an adverse-event rate, and it is not a causal verdict.[^eadv][^medpage]
The most important result came later in the analysis. Adjustment for age, sex, country, comorbidities, and nutritional deficiencies weakened—but did not erase—the associations. Yet when investigators restricted the analysis to new-onset lesions, the associations disappeared: onycholysis had an adjusted odds ratio (aOR) of 1.0 (95% confidence interval 0.6–1.7), and dyschromia had an aOR of 0.9 (0.6–1.3).[^medpage]
That contrast is the real story. The study detected a cross-sectional nail signal worth investigating. It did not show that treatment created those nail changes.
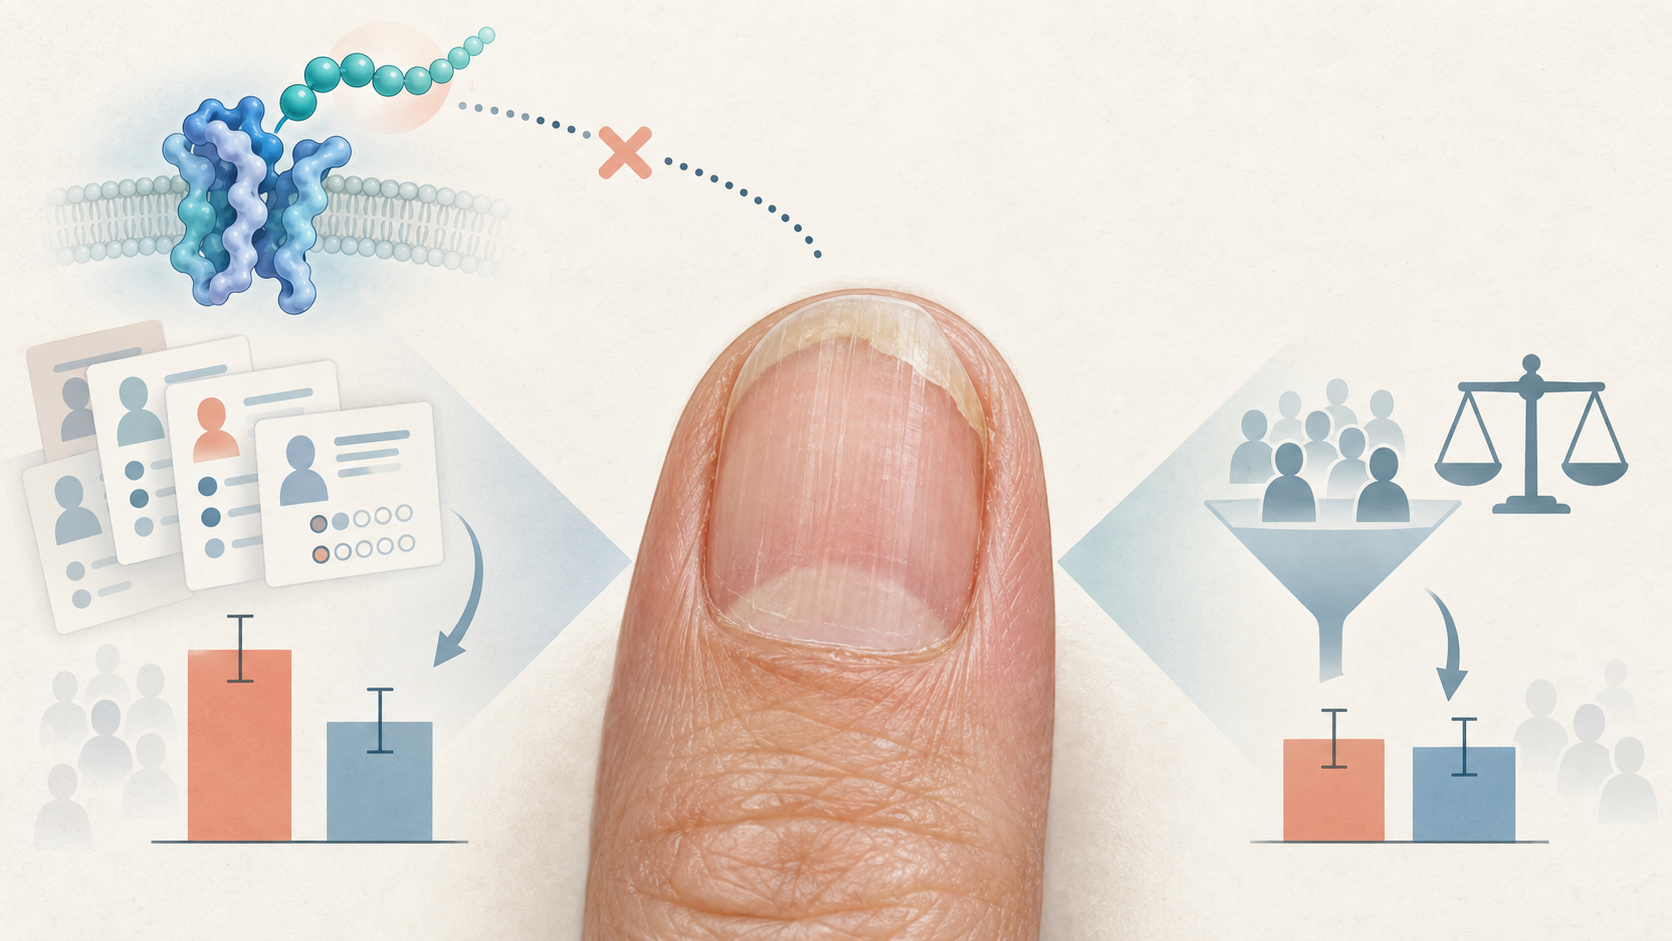
The crude survey comparison showed a large gap. Restricting the analysis to nail changes that began after treatment removed the association, which sharply limits a causal interpretation.
Quick answer: do GLP-1 drugs cause nail detachment?
The available nail study cannot answer that question causally. It compared the prevalence of self-reported nail findings among 575 GLP-1 receptor-agonist users and 1,329 non-users recruited in France, the United States, Brazil, and Mexico. Both groups had obesity, type 2 diabetes, or both.[^eadv][^emj]
Three findings should be read together:
- Crude prevalence: onycholysis was reported by 39.3% of users versus 8.7% of non-users.
- Adjusted models: the onycholysis association fell to aOR 2.9 (2.2–3.9) after adding comorbidities and nutritional deficiencies.
- New-onset sensitivity analysis: the onycholysis association was null at aOR 1.0 (0.6–1.7).
The first number makes the headline. The third determines how cautious the headline must be.
What did the EADV nail study actually find?
GLP-1 users reported several nail findings more often than non-users at the time of the survey. The main crude comparisons were:[^medpage]
| Survey finding | GLP-1 users | Non-users | What it means | |---|---:|---:|---| | Onycholysis (nail separation) | 39.3% | 8.7% | Prevalence among respondents, not incidence caused by treatment | | Dyschromia (nail discoloration) | 45.6% | 17.0% | Same cross-sectional limitation | | Any nail disorder | 66.3% | 52.8% | Broad composite that combines different nail problems |
Onycholysis means separation of the nail plate from the nail bed. It can have many causes, including trauma, fungal disease, inflammatory skin disease, thyroid disease, medications, and other systemic factors. Dyschromia is similarly broad: it describes altered nail color, not one diagnosis or mechanism.
The percentages therefore describe what respondents reported, not how many people developed a confirmed drug reaction after beginning a specific GLP-1 product.
Why is 39.3% versus 8.7% not an adverse-event rate?
Because this was a prevalence comparison rather than an incidence study with a verified treatment start and prospective follow-up. Prevalence asks, “Who has or reports the condition at the survey time?” Incidence asks, “Who newly developed the condition during a defined period after a clear baseline?”
That distinction matters here because about half of GLP-1 users reported nail problems that predated treatment. A pre-existing lesion can be counted in cross-sectional prevalence even though the drug could not have initiated it.
Calling 39.3% an adverse-event rate would imply a documented sequence: treatment began, the nail was initially unaffected, the lesion appeared afterward, and competing causes were assessed. The survey did not establish that sequence for the crude result.
Evidence-literacy rule: A large difference in current prevalence can reveal a signal. It cannot, by itself, reveal when the condition began or what caused it.
What happened after statistical adjustment?
Adjustment reduced the estimates, showing that baseline differences explained part—but not necessarily all—of the crude gap. The published conference reporting described a staged analysis:[^medpage]
| Analysis | Onycholysis | Dyschromia | |---|---:|---:| | Adjusted for age, sex, and country | aOR 4.4 (3.3–5.8) | aOR 3.3 (2.6–4.2) | | Added comorbidities and nutritional deficiencies | aOR 2.9 (2.2–3.9) | aOR 2.2 (1.7–2.8) | | Restricted to new-onset lesions | aOR 1.0 (0.6–1.7) | aOR 0.9 (0.6–1.3) |
An adjusted odds ratio is a model-based comparison after accounting for listed variables. It is not a corrected percentage, and it does not prove that every important difference was measured.
The attenuation is informative. The exposed group was younger on average—45.3 versus 56.7 years—and could differ in disease severity, healthcare use, nutrition, weight-loss trajectory, dermatologic history, and reasons for receiving treatment. Adjustment can address recorded variables. It cannot remove unknown factors, poorly measured factors, or misclassified self-reports.
Why does the null new-onset analysis matter most?
Causality requires the proposed cause to precede the outcome, so a new-onset analysis is more relevant than a snapshot containing old lesions. In that sensitivity analysis, the confidence intervals included 1.0 and the point estimates were essentially null for both onycholysis and dyschromia.
That does not prove the drugs have no nail effect. Sensitivity analyses may have fewer eligible events, less precision, and imperfect recall about when a lesion began. But it directly tests a major causal requirement that the crude comparison does not.
The discrepancy supports several possibilities:
- Much of the crude gap came from nail problems that existed before treatment.
- Users and non-users differed in other ways the models did not fully capture.
- Self-report or recall differed between groups.
- A smaller treatment-related effect exists but this design could not isolate it.
- Different products, treatment durations, weight changes, or nutritional states produced heterogeneous effects that a class-wide survey blurred together.
The defensible conclusion is “unresolved signal,” not “fourfold causal risk.”
What limits this cross-sectional online survey?
The design is useful for generating hypotheses but weak for estimating causal adverse-event rates. Its main limitations are:
- Cross-sectional timing: exposure and outcome were assessed around the same survey, so temporal order is uncertain.
- Self-report: participants described nail problems without standardized dermatologist confirmation for every respondent.
- Online recruitment: people who notice symptoms may be more likely to participate or report them.
- Baseline imbalance: the groups differed in age and likely in treatment selection, disease history, and healthcare contact.
- Pre-existing nail disease: roughly half of users reported nail problems before GLP-1 treatment.
- Exposure heterogeneity: “GLP-1 receptor agonist use” combines different drugs, doses, durations, indications, and patterns of weight change.
- Outcome heterogeneity: onycholysis and dyschromia each have multiple causes, while “any nail disorder” is broader still.
- Residual confounding: nutritional deficiency, dermatologic disease, trauma, fungal infection, endocrine disease, medication use, and other factors may be incompletely measured.
The investigators reported that analyses among people who lost weight produced similar staged estimates. That weakens a simple claim that weight loss alone explains everything. It still does not identify a direct drug mechanism.
Is this the same signal as GLP-1-related hair loss?
No. Nail findings and alopecia are separate outcomes supported by different studies. A 2026 BMJ article evaluated incident alopecia using electronic health records and a target-trial emulation with active drug comparators. It included treatment initiators, follow-up over time, and much larger comparison cohorts.[^bmj]
That peer-reviewed analysis found a low-frequency association between GLP-1 receptor agonists and alopecia compared with SGLT-2 and DPP-4 inhibitors. It still could not prove causation, but its longitudinal new-user design answers timing more directly than this nail survey.
PeptideBase covers that evidence separately in Do GLP-1 Drugs Cause Hair Loss? What the New BMJ Study Actually Shows. Combining the two signals into “GLP-1 drugs damage hair and nails” would erase important differences in outcome definition, study design, absolute frequency, and evidentiary strength.
For a broader guide to source quality, see GLP-1 Side Effects: What Trials, Labels, and Online Communities Can Each Tell Us.
How strong is a conference abstract or press release?
It is early evidence, not the final version of the study. Conference reporting can surface timely data, sample sizes, model estimates, and expert discussion. It usually does not provide the complete protocol, questionnaire, missing-data handling, exposure definitions, full subgroup tables, preregistered analysis plan, or peer-review history available in a journal article.
The EADV press release states that the work was conducted with institutional support from DUCRAY Laboratories, part of the Pierre Fabre Group.[^eadv] That support and the authors’ congress disclosures belong in the evidence record. They do not automatically invalidate the results, but they make full methods, prespecified analyses, data transparency, and a detailed journal conflict-of-interest statement especially important.
The public conference materials available for this review did not provide disclosure detail equivalent to a full peer-reviewed article. Until a complete paper appears, uncertainty about methods and individual relationships should remain explicit rather than silently treated as resolved.
What would a stronger prospective study need to show?
A convincing study would begin before treatment and document incident, clinically verified nail changes over time. At minimum, it would need:
- standardized baseline nail examinations before the first exposure;
- serial clinical photography and onychoscopy using blinded or independent assessment;
- product-specific exposure, duration, adherence, indication, and weight-change data;
- laboratory monitoring relevant to iron, zinc, vitamin B12, vitamin D, protein status, thyroid function, and other plausible contributors;
- assessment of trauma, manicures, fungal disease, psoriasis, eczema, thyroid disease, and concomitant medications;
- a prespecified definition of incident onycholysis and dyschromia;
- an appropriate active comparator group and adequate follow-up;
- transparent handling of missing data and loss to follow-up;
- enough events to analyze individual drugs rather than treating the class as uniform;
- independent replication and full funding/conflict disclosures.
A randomized trial designed around nail outcomes would offer stronger causal leverage, but may be impractical for an uncommon or delayed dermatologic event. A carefully designed prospective dermatology cohort could still move the evidence substantially beyond an online cross-sectional survey.
Bottom line
The EADV report found a real and striking prevalence difference, but its best timing-focused analysis did not find more new-onset onycholysis or dyschromia among GLP-1 users. The fourfold headline describes the crude cross-sectional snapshot. It does not describe a proven drug-caused event rate.
The signal deserves prospective study with baseline examinations, standardized onychoscopy, product-specific exposure data, biological monitoring, and transparent disclosure. Until then, the evidence supports careful investigation—not a causal verdict.
This article is for general education only. It does not provide medical advice, diagnosis, treatment guidance, dosing guidance, discontinuation guidance, or recommendations to start, stop, switch, source, or purchase any medication.
Frequently asked questions
What is onycholysis?
Onycholysis is separation of the nail plate from the nail bed. It is a finding with multiple possible causes, not a diagnosis that identifies one cause by itself.
Did 39.3% of GLP-1 users develop nail detachment because of the drug?
No. The 39.3% figure was the prevalence reported among surveyed users. It included people whose nail problems may have begun before treatment and should not be read as an incidence or causal adverse-event rate.
What did the new-onset analysis find?
It found no association for the two headline outcomes. The aOR was 1.0 (0.6–1.7) for onycholysis and 0.9 (0.6–1.3) for dyschromia.
Does statistical adjustment prove a direct drug effect?
No. Adjustment can reduce measured confounding, but it cannot remove unmeasured or poorly measured differences. The estimate also changed substantially when the analysis focused on lesions that began after treatment.
Has this nail study been peer reviewed?
The results discussed here were presented at EADV Congress 2026 and reported through conference and press materials. That is weaker than a complete peer-reviewed prospective dermatology study with full methods and disclosures.
[^eadv]: European Academy of Dermatology and Venereology. “Nail detachment over four times more common among GLP-1 users, first controlled study finds.” EADV Congress 2026 press release, October 1, 2026. https://eadv.org/wp-content/uploads/2026/09/EADV_2026_Bruno_GLP1_Press_Release_01_10.pdf [^medpage]: MedPage Today. “GLP-1s Tied to Detached Fingernails in New Study.” October 1, 2026. https://www.medpagetoday.com/meetingcoverage/eadv/123238 [^emj]: European Medical Journal. “GLP-1 Nail Disorders More Common in Multinational Study: EADV 2026.” October 2026. https://www.emjreviews.com/dermatology/news/glp-1-nail-disorders-more-common-in-multinational-study-eadv-2026/ [^bmj]: Tang H, et al. “Risk of hair loss associated with glucagon-like peptide-1 receptor agonists in adults with type 2 diabetes: target trial emulation.” BMJ. 2026;394:e100077. https://doi.org/10.1136/bmj-2026-100077